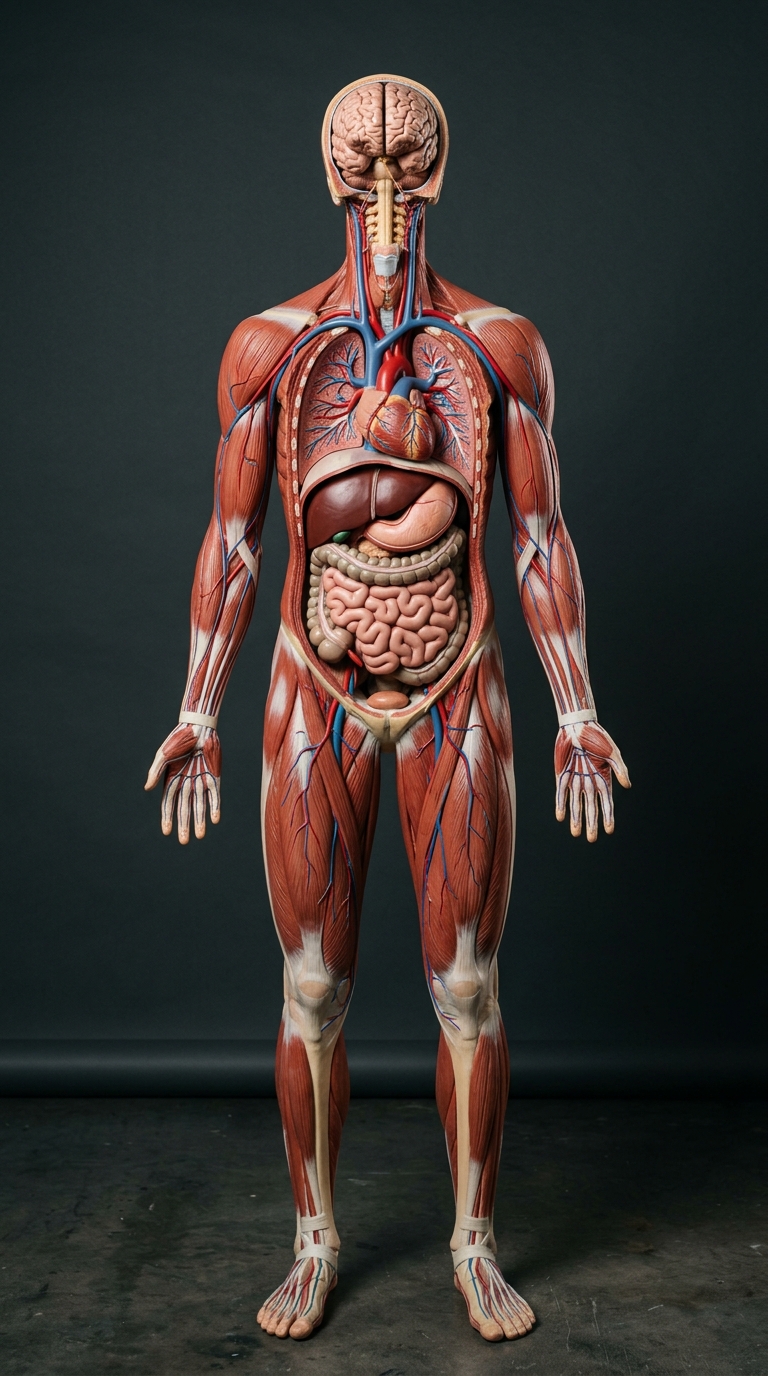
See how each organ ages, what to measure, and where to begin.
Filter by focus
Focus:
Body atlas
Active View: Brain & Cognition
View organ details ↓Press 1-8 to choose an organ. Esc resets the view.Tap a pin to explore.
NEUROLOGICAL HEALTHBody atlas
Brain & Central Nervous System
Cognitive reserve, synaptic plasticity, and slow-wave waste clearance.
Perfusion Rate750 mL / min
Energy Demand20% Whole Body
Glymphatic Window02:00 - 04:00 AM
Compare tissue aging +
Cellular Tissue Inspector
PHYSIOLOGICAL PEAKOptimal youthful function
High synaptic density, intact blood-brain barrier integrity, active neurogenesis in the dentate gyrus, and pulsatile clearance of metabolic waste during slow-wave sleep.
How it ages
As we age, microvascular blood flow to the brain decreases, synaptic density diminishes, and chronic microglial neuroinflammation rises. Crucially, the glymphatic waste system (which pulses cerebrospinal fluid through the brain during deep slow-wave sleep) becomes less efficient, permitting misfolded amyloid-beta and hyperphosphorylated tau proteins to aggregate.
Glymphatic Sleep Optimization: 7.5 to 8.5 hours in complete darkness and a cool environment (19°C / 66°F). Side-sleeping (lateral posture) maximizes gravitational and pulsatile cerebrospinal waste flush.
BDNF Aerobic Induction: 35-45 minutes of steady Zone 2 cardio paired with weekly high-intensity intervals triggers massive increases in circulating BDNF, stimulating hippocampus neurogenesis.
Heat Shock Protein Response: 20 minutes in a dry Finnish sauna (80°C) 4 to 7 times weekly is associated with a 66% lower risk of Alzheimer’s and dementia (Kuopio Ischemic Heart Disease Study).
Continuous Cognitive Demand: Actively learning unfamiliar motor-cognitive skills (new languages, instruments, ballroom dance, or tennis) forces novel neural pathway formation.
02Primary mortality drivers
The Four Diseases That Cause 80% of Adult Deaths
For individuals over age 50 who do not smoke, the vast majority of mortality is caused by four slow-developing chronic conditions. Longevity medicine is about delaying their biological onset by 10 to 20 years.
01
Cardiovascular#1 Global Killer
Atherosclerotic Heart Disease (ASCVD)
Caused by circulating ApoB-containing lipoproteins that penetrate the endothelial arterial wall, oxidize, and trigger calcified plaque over decades until blood flow to the heart or brain is obstructed.
Primary Diagnostic:ApoB particle count + CAC scan
Longevity Target:ApoB < 60 mg/dL • CAC Score: 0
02
Oncology#2 Global Killer
Cancer & Somatic Mutation
Driven by cumulative DNA replication errors, oxidative damage, and the gradual decline of immune surveillance that allows mutated rogue cells to escape apoptosis and proliferate unchecked.
Progressive synaptic loss, microglial neuroinflammation, and failure of glymphatic waste clearance during deep sleep, leading to amyloid-beta aggregation and hyperphosphorylated tau tangles.
The underlying catalyst that accelerates the other three diseases. Driven by ectopic fat spilling into the liver and pancreas, chronic hyperinsulinemia, and endothelial glycocalyx erosion.
This illustration explores healthier aging. It cannot predict your lifespan, years of illness or need for care.
04CARDIORESPIRATORY BIOMARKERFitness and longevity
VO2 Max & All-Cause Mortality Hazard Curve
Higher fitness was associated with lower mortality in an observational study of 122,007 patients. This curve is an illustration, not a personal risk assessment.
Your inputs
Drag to adjust
40 years
44.0 mL/kg/min
Apple Watch / Garmin / Lab
Cooper 12-min Run Equiv
~2,450meters
ALL-CAUSE MORTALITY HAZARD RATIO
1.41x
ElevatedRelative Risk (vs. Elite Baseline HR 1.0)
Hazard curveYou
VO2 Max (mL / kg / min)Shaded bands follow your age and sex cohort
Cohort percentile65th Percentile
ABOVE AVERAGE
025th50th75th97.5th
Low<25th
Below average25th-49th
Above average50th-74th
High75th-97th
Elite>97.5th
This input falls in the model's above average range. Higher fitness is associated with lower mortality, but this does not quantify your personal risk.
EXAMPLE TRAINING STRUCTURE:
Norwegian 4x4 Intervals: Perform 1 weekly session (4 minutes at 90-95% max HR, followed by 3 minutes active recovery, repeated 4 times). Paired with 150 minutes of Zone 2 steady cardio, this induces rapid mitochondrial biogenesis and expands stroke volume by 0.5-1.0 mL/kg/min per month.
Session structure4 x 4 min work, 3 min recovery
90-95% max HRActive recovery
05CARDIOVASCULAR RISK MODELArea-Under-The-Curve
Lifetime ApoB Atherosclerosis Exposure Projector
Lower ApoB over time can reduce cardiovascular risk. This chart illustrates exposure, not plaque volume or event timing. Its 9,000 reference is not a clinical threshold. Read the evidence.
Your inputsDrag to adjust
Burden at 806,660 mg·yr30.6% less
120 mg/dL
Average adult baseline is 100-130 mg/dL without lipid management.
38 years
Earlier lipid lowering can reduce cumulative exposure. Treatment depends on individual risk.
50 mg/dL
Optimal longevity target is < 60 mg/dL (achievable with diet + statin/ezetimibe/PCSK9i).
AUC = ApoB × Age
Cumulative exposure curveIllustrative ApoB exposure by age, mg·years/dLUntreatedWith interventionModel reference
MODELED APOB EXPOSURE AT AGE 80
6,660mg·years/dL
30.6%less
30.6% Lifetime Exposure Reduction
MODEL REFERENCEBelow reference
Below reference at age 80Unchanged inputs: Model reference reached at age 75
Lifetime exposure at 80Shared scale
Untreated Natural Trajectory9,600 mg·yr (Above Model Reference)
With Early Intervention at Age 386,660 mg·yr (Below Reference at Age 80)
9,000 Model Reference
Clinical Takeaway:
Lower ApoB reduces modeled exposure through age 80. Cardiovascular risk also depends on other factors.
Circadian biology governs gene transcription, cellular repair, hormonal pulses, and metabolic clearance. Select your individual lifestyle archetype below to generate an actionable, hour-by-hour operational schedule backed by peer-reviewed clinical science.
Choose an archetypeArrow keys switch
Circadian dialHigh-Stress Professional
Protocol phases
Feeding window
Sleep
Primary ObjectiveAutonomic Nervous System Balance & Cortisol Taper
Circadian Anchor06:30 AM Light Exposure / 22:30 PM Sleep
Feeding Window10:00 AM - 18:30 PM (16:8 Time-Restricted)
Hour-by-hour scheduleDawnNight
07QUANTITATIVE ASSESSMENT
Lifestyle aging illustration
Explore an illustrative model of sleep and movement. It does not measure biological age, predict lifespan or diagnose health. Clinical PhenoAge requires blood biomarkers and is not calculated here.
Illustrative age31.8 yrs0.84x pace
Your inputsDrag to adjust
38 years
Your age sets the baseline for this illustration.
180 mins / wk
Aerobic activity supports fitness. This model does not measure changes in biological aging.
7.5 hours
Under 6 hours nightly doubles cardiovascular event risk and impairs cellular waste clearance.
3 days / wk
Preserving lean muscle mass and grip strength is the single best defense against physical frailty past age 60.
Model contributionsLowerHigher
Zone 2 cardio-
Sleep-
Strength-
YOUR ILLUSTRATIONLifestyle model
Illustrative age
31.8years
vs 38 chronological
Model vs chronological age
6.2 Years Below the Model Baseline
Chronological38 yrs
Illustrative31.8 yrs
Illustrative Pace Index
LowerBaselineHigher
0.84x (Below baseline)A model index, not a measured rate of aging.
Illustrative Healthspan91 Years
Now
LivedModel years ahead
An illustration, not a forecast of healthy years.
Key Priority for You:
Regular aerobic activity supports fitness. Build a routine that fits your ability and health.
LONGEVITY BAE - PREVENTATIVE LAB PANEL
Official Reference: longevitybae.com
Date: ___________________
Patient: ___________________
Physician: ___________________
Please consider authorizing the following advanced preventative biomarkers during this physical exam.
08ACTIONABLE CLINICAL TOOLTake to Your Doctor
The Longevity Blood Panel: Tests to Request
Standard annual physicals typically only order basic total cholesterol and fasting glucose, which can miss early cardiovascular and metabolic disease by a decade. Bring this checklist to your physician to request the tests that actually measure lifespan drivers.
Tick the tests you want to raise
Print a clean sheet
Bring it to your appointment
Lab requisitionPreventative biomarker panel
Selections are saved on this device
0/7
Marked for discussion0 of 7 tests marked for discussion
Ask
Biomarker
Standard Range
Optimal Longevity Target
Clinical Significance
Guide
01Superior to LDL-C
< 90 mg/dL
< 60 mg/dL
Directly measures the number of atherogenic, plaque-causing particles in your bloodstream.
Pathophysiological Mechanism:
Every circulating ApoB lipoprotein particle can cross into the arterial sub-endothelial space. Once trapped, it oxidizes and triggers sterile inflammation, macrophage recruitment, and calcified fibrous plaque growth.
Every 6 to 12 months until target (< 60 mg/dL) is achieved; annually thereafter.
02Genetically determined
< 75 nmol/L
< 30 nmol/L
Independent genetic risk factor for early heart attack and stroke. Only needs to be tested once in life.
Pathophysiological Mechanism:
Lp(a) contains an ApoB molecule covalently bound to apolipoprotein(a), which resembles plasminogen and promotes vascular thrombosis while aggressively depositing oxidized phospholipids into vascular walls.
First-Line Interventions:
Genetically fixed (diet changes have minimal effect). If elevated (> 100 nmol/L), aggressively drive other risk factors to absolute minima: target ApoB < 50 mg/dL and blood pressure < 120/80 mmHg.
Testing Frequency:
Once in a lifetime (levels remain stable across adulthood).
03Early metabolic warning
< 20 µIU/mL
< 5 µIU/mL
Spikes up to 10 years before fasting glucose rises, detecting insulin resistance at the reversible stage.
Pathophysiological Mechanism:
Chronically elevated insulin drives ectopic fat accumulation in the liver, accelerates systemic endothelial damage, impairs sodium excretion (raising blood pressure), and shuts down cellular autophagy.
First-Line Interventions:
Eliminate refined carbohydrates and liquid sugars; adopt 16:8 time-restricted feeding; perform post-meal 10-minute walks; lift heavy weights 3x/week to trigger non-insulin glucose disposal via GLUT-4.
Testing Frequency:
Every 3 to 6 months to evaluate metabolic interventions.
04Vascular inflammation
< 3.0 mg/L
< 0.5 mg/L
Quantifies low-grade systemic vascular inflammation that destabilizes arterial plaques and promotes decline.
Pathophysiological Mechanism:
High-sensitivity C-reactive protein is an acute-phase reactant synthesized by the liver in response to interleukin-6. It reflects chronic sterile vascular inflammation that weakens fibrous caps over plaques, precipitating heart attacks.
Annually, or every 6 months during active anti-inflammatory protocol changes.
053-Month glucose average
< 5.7%
< 5.2%
Reflects glycosylation of red blood cells. Lower levels reduce advanced glycation end-products (AGEs).
Pathophysiological Mechanism:
Glycation of hemoglobin reflects whole-body exposure to elevated blood glucose. Chronic glucose excursions cross-link extracellular collagen, stiffen coronary arteries, and damage renal microvasculature.
First-Line Interventions:
Pair carbohydrates with soluble fiber and healthy fats; engage in Zone 2 aerobic base training to expand mitochondrial fat-burning capacity; supplement berberine or alpha-lipoic acid if indicated.
Testing Frequency:
Every 3 to 6 months (reflects red blood cell lifespan of ~120 days).
06Methylation & vascular health
< 15 µmol/L
< 9 µmol/L
Elevated levels damage endothelial lining and correlate with cognitive decline; easily modulated with B vitamins.
Pathophysiological Mechanism:
An intermediate sulfur amino acid in the methionine-cysteine cycle. When methylation cofactors are deficient or MTHFR variants are present, homocysteine accumulates, stripping nitric oxide and promoting cerebral white matter hyperintensities.
Critical for thousands of gene transcription pathways, immune defense, and bone mineral density preservation.
Pathophysiological Mechanism:
A secosteroid hormone that binds to the nuclear Vitamin D Receptor (VDR) across nearly every human tissue. Maintains calcium homeostasis, suppresses autoimmune self-reactivity, and protects bone mineral matrix.
First-Line Interventions:
Daily oral Vitamin D3 (2,000 - 5,000 IU) paired synergistically with Vitamin K2 (MK-7 100 µg) and magnesium to direct calcium into bones and teeth rather than arterial vascular walls.
Testing Frequency:
Every 6 months (especially at end of winter and end of summer).
Tick the tests you want to raise, then print a clean sheet for your appointment.Press P to print
Physician Discussion & Follow-Up Notes:
PEER-REVIEWED EVIDENCE BASE
Primary Clinical Studies & Methodologies
Read the studies behind these topics. Interactive scenarios are illustrations, not validated predictions or clinical assessments.
JAMA Network Open2018n = 122,007
Association of Cardiorespiratory Fitness With Long-term Mortality Among Adults Undergoing Exercise Treadmill Testing
Mandsager K, Hurley S, Tcheandjieu C, et al. (Cleveland Clinic)
Elite cardiorespiratory fitness (VO2 Max > 97.5th percentile) was associated with an 80% reduction in all-cause mortality (HR 0.20) compared with the lowest performers. Cardiorespiratory fitness was a stronger predictor of mortality than smoking, diabetes, or coronary artery disease.
Low-Density Lipoproteins Cause Atherosclerotic Cardiovascular Disease: Evidence From Genetic, Epidemiologic, and Clinical Studies
Ference BA, Ginsberg HN, Graham I, Ray KK, Packard CJ, et al.
Demonstrates that the causal effect of ApoB-containing lipoproteins on the risk of ASCVD is determined by both the absolute magnitude and the cumulative lifetime duration of exposure.
Men reporting 4 to 7 sauna sessions per week had a 63% lower risk of sudden cardiac death and a 40% lower risk of all-cause mortality compared with men who used the sauna once weekly. Follow-up papers documented a 66% reduction in dementia.
DunedinPACE measures the instantaneous speed of biological decay rather than accumulated chronological years. Faster DunedinPACE scores predict accelerated functional decline, morbidity, and premature mortality.
An Epigenetic Biomarker of Aging for Lifespan and Healthspan (Phenotypic Age)
Levine ME, Lu AT, Quach A, Chen BH, et al.
Developed a clinical biomarker algorithm integrating albumin, creatinine, glucose, hs-CRP, lymphocyte percentage, mean corpuscular volume, red cell distribution width, alkaline phosphatase, and white blood cell count into a composite biological age metric.
Apolipoprotein B Particles and Cardiovascular Risk: A Pathophysiological Review
Sniderman AD, Thanassoulis G, Glavinovic T, Navar AM, Pencina M, et al.
Confirms that ApoB provides superior predictive accuracy over LDL cholesterol, total cholesterol, or non-HDL-C because each atherogenic particle carries exactly one molecule of ApoB.